Your care team faces medication access barriers every day — without the capability to navigate them.

One structured system protects your patients, staff and budget

Practical capability building for prior authorization, appeals, and medication access barriers.

MedAccessCE™ closes the institutional knowledge gap — structured curriculum that equips every prescriber and nurse on your team with the frameworks, templates, and decision tools to cut through barriers at the point of care.

Every denial, every delay, every abandoned prescription is a patient who didn't get their medication.

Evidence-based access tools for the care team.

Three ways to close the gap

One structured system. Three tools, built for different depths of need.

Certificate Courses

Foundational training. Build the knowledge behind every access barrier your team faces — 12 modules covering PBM structures, payer dynamics, drug shortages, rare disease funding, and patient advocacy. The training your staff should have had on day one.

Best for: institutional knowledge that outlasts any one hire.

Enroll on Thinkific

Clinical Operations Package

Broad point-of-care toolkit. Ready-to-use smart phrases and fill-in-the-blank templates for every access barrier — prior authorization, drug shortages, pharmacy deserts, rare disease funding — updated twice a year so your team is never working from outdated payer logic.

Best for: equipping your whole team with a fast, correct answer no matter which barrier hits.

License the Clinical Operations Package for Your Health System

Prior Authorization Reference Guide

Deep medication-specific reference. Diagnosis codes, payer criteria, and ready-to-use appeal language for 76 high-volume medications — built for staff who fight the same drug-specific denials every week and need the case built before they pick up the phone.

Best for: high PA-volume practices and specialists who need drug-level detail, fast.

Get the Prior Authorization Reference Guide
See inside the Clinical Operations Package

Real Denial. Real Letter. Real Fast.

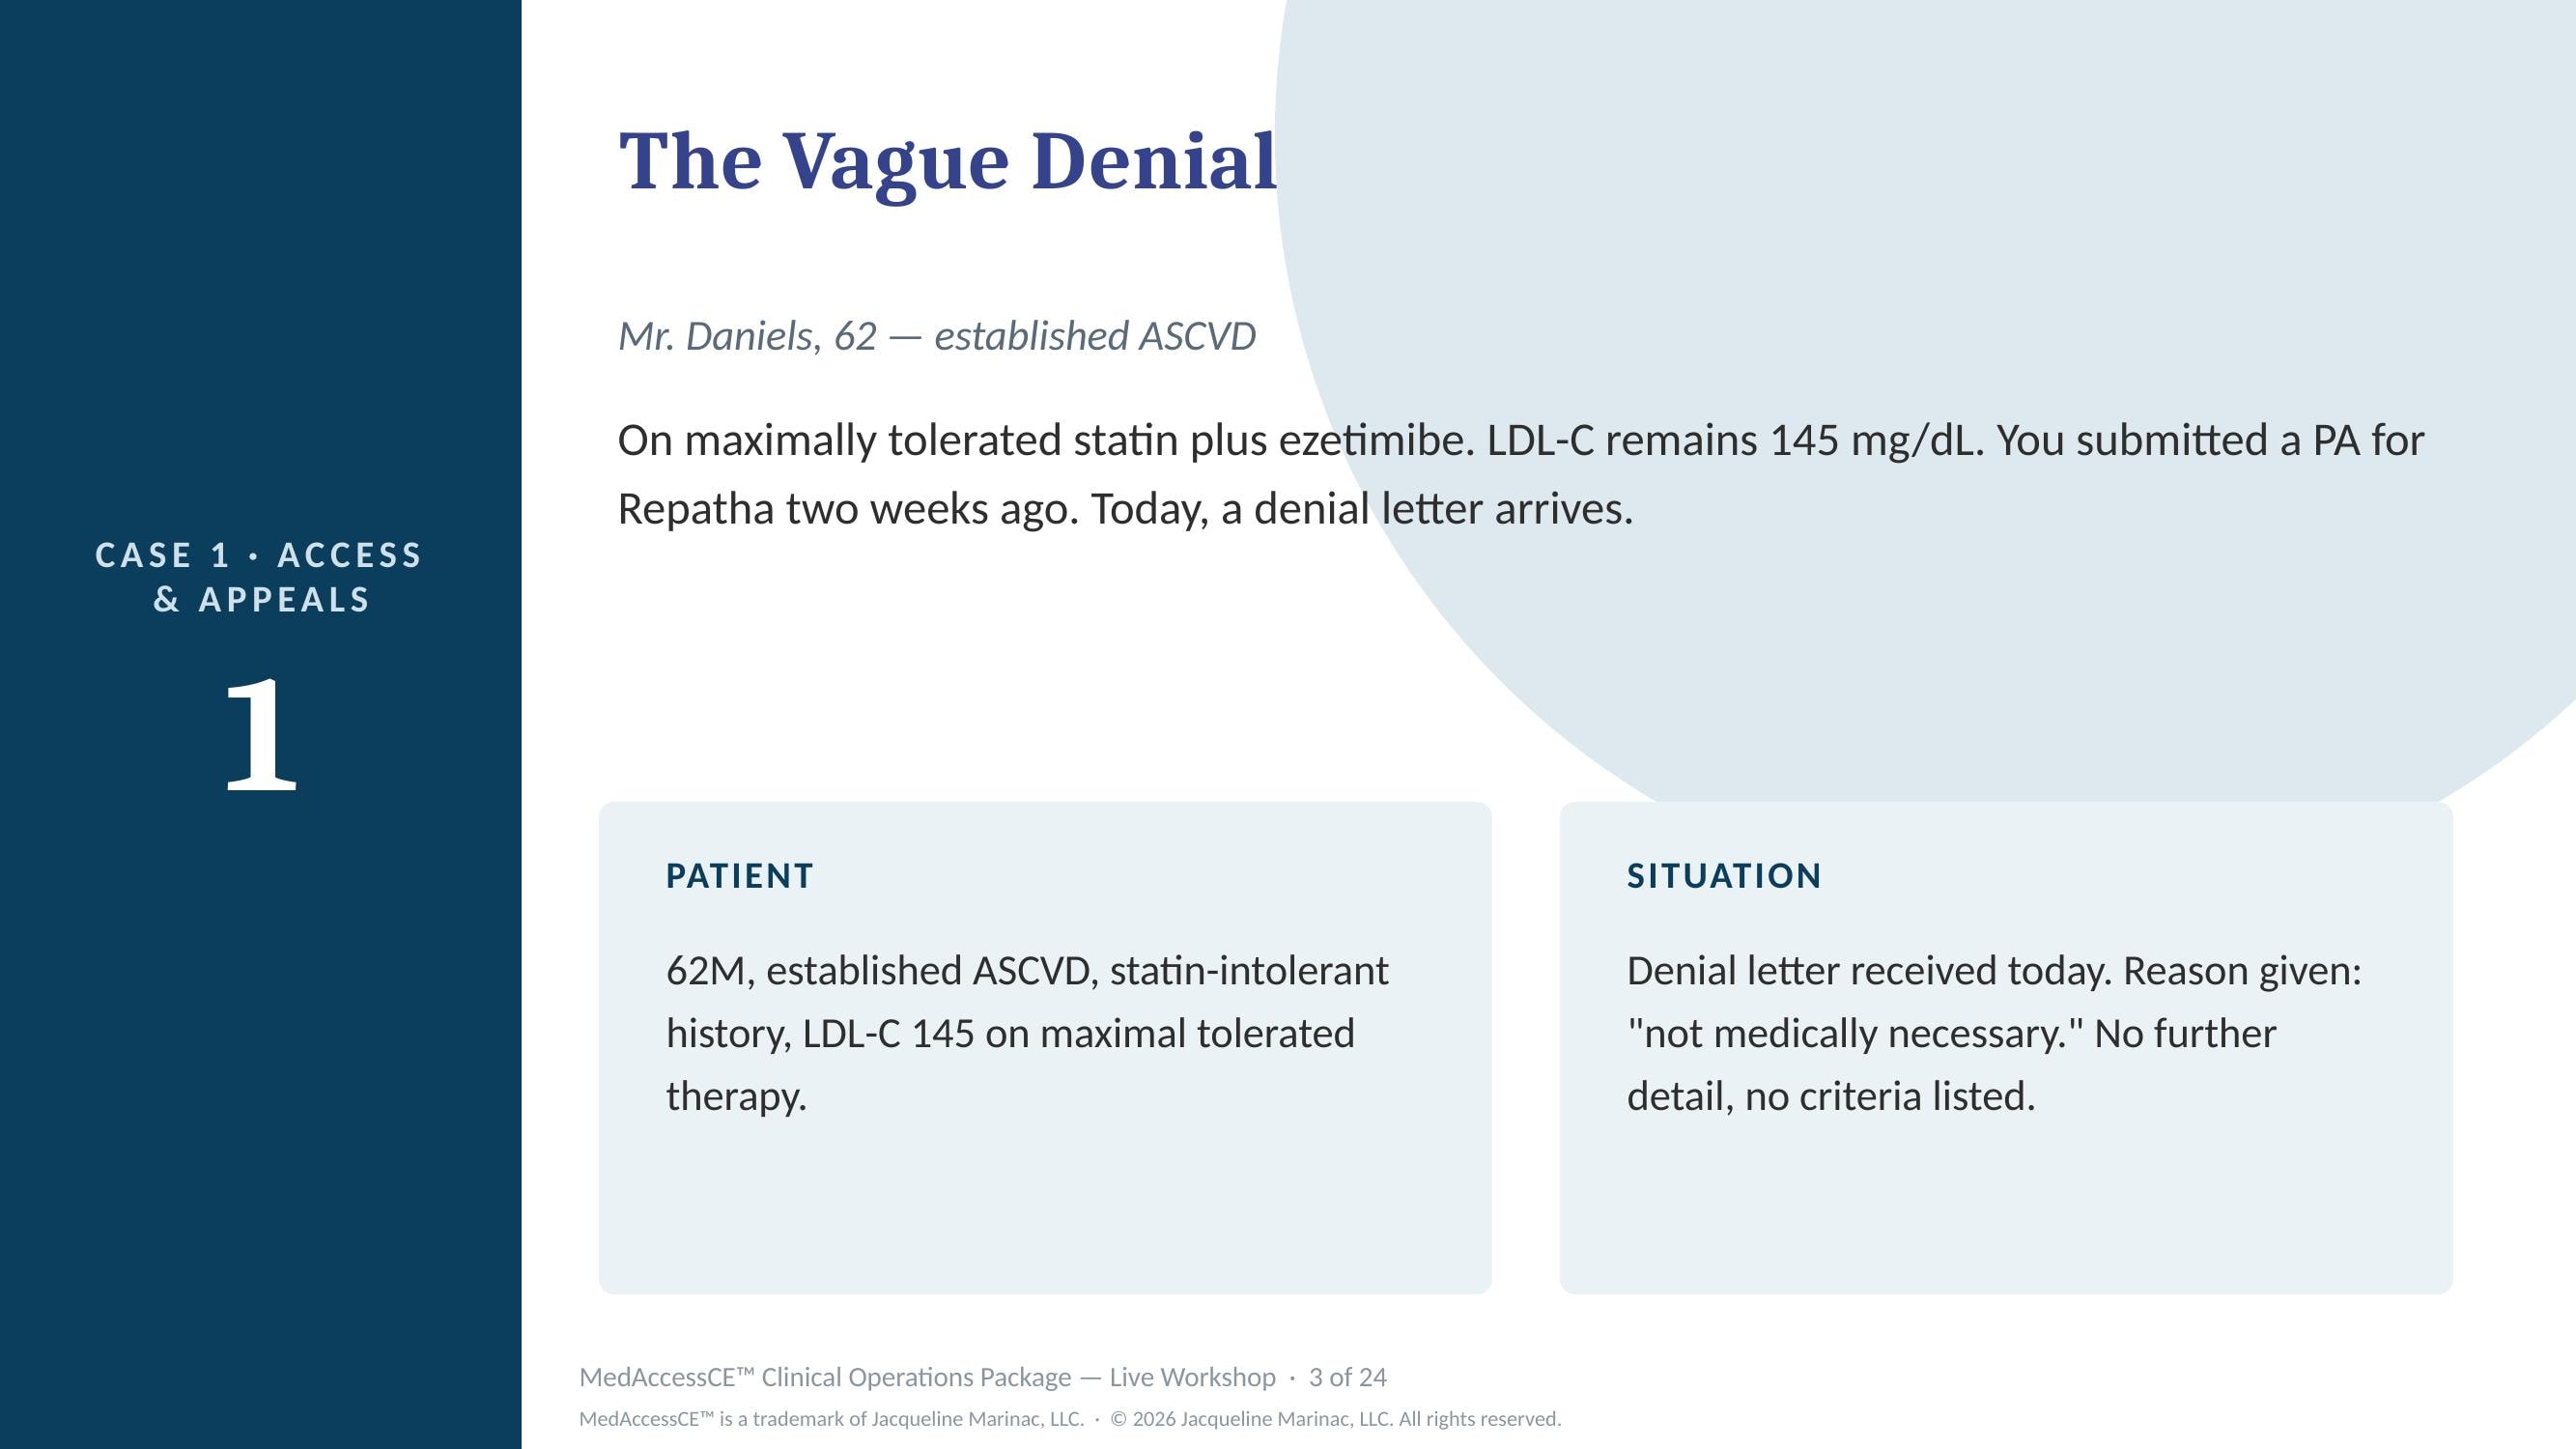
Every section of the Clinical Operations Package follows the same pattern — a real barrier, and the real fill-in-the-blank template that solves it. Here's Case 1.

The Problem

A denial letter that just says "not medically necessary" — with nothing else.

Case 1: The Vague Denial — a prior authorization denial letter that says only 'not medically necessary' with no further detail
The Solution

The actual appeal letter template from Section 2 — verbatim, fill-in-the-blank, ready to fax today.

Case 1: First-level appeal letter template from Section 2 — fill-in-the-blank, verbatim, ready to fax today
Prior Authorization Reference Guide

Real Drug. Real Criteria. Real Appeal.

The Prior Authorization Reference Guide applies the same fix, one medication at a time. Here's a real example from the guide.

The Problem

Eosinophil count not documented or below payer threshold — a common denial reason for the asthma biologic Fasenra (benralizumab).

The Solution

The patient has severe eosinophilic asthma with recurrent exacerbations despite maximized inhaled maintenance therapy. Benralizumab (Fasenra) is medically necessary to reduce exacerbation frequency and oral corticosteroid burden.

Ready to use, verbatim, from the guide.

Get the Prior Authorization Reference Guide
The prior authorization burden

The prior authorization burden isn't a workflow problem. It's a training gap.

Medication access work has become one of the largest non-clinical time drains in modern practice. Prior authorizations, step therapy exceptions, formulary appeals, and denial management now consume hours that should go to patients — and most care teams are navigating it without structured training or purpose-built tools.

According to the American Medical Association's 2025 Prior Authorization Physician Survey of 1,000 physicians, physicians report an average of 39 to 40 prior authorization requests per week. Roughly half of that volume is for prescription medications — an estimated 19 to 20 medication-specific prior authorizations per prescriber, every week.* The same 2025 AMA survey found that physicians and their staff spend an average of 13 hours a week on prior authorization overall. More than one in five physicians — 22%, per AMA — spend over 20 hours a week on it. Four in ten physicians (40%, per AMA) now have staff dedicated exclusively to prior authorization work. That is not inefficiency. That is a system absorbing a workforce.

Clinicians who have been trained in payer logic, appeals language, and PA workflow — and who have the right tools at hand — move through this work differently. Requests are structured correctly the first time. Appeals are filed with the clinical language that actually moves payers. Denials that would have been abandoned get resolved. The work doesn't disappear, but it stops consuming the day.

MedAccessCE™ has no ownership, licensing, or revenue relationship with any payer, pharmacy benefit manager, drug manufacturer, or EHR vendor. The training reflects what the evidence and clinical experience support — not what any commercial partner benefits from teaching.

Source: American Medical Association. 2025 AMA Prior Authorization Physician Survey. AMA; 2025.
* Derived estimate: no source publishes a medication-only weekly PA count directly. This figure applies the ~50% prescription-medication share of total PA volume (reported in an earlier AMA survey wave) to the 39–40 total PAs/week figure from the 2025 AMA survey. See the full derivation, source list, and known limitations in the ROI Calculator methodology notes.

Jacqueline S. Marinac, PharmD, CCRC — Founder of MedAccessCE™

PharmD, CCRC

Founder & Author

PharmDCCRC — Certified Clinical Research Coordinator30+ Years Clinical Education Experience
Clinician-built. Not consultant-designed.

Built by a pharmacist who lived the access fight.

Jacqueline S. Marinac, PharmD, CCRC spent years watching patients lose access to medications they needed — not because the drugs didn't exist, but because no one on the care team had the tools to fight back. Prior authorizations denied. Drug shortages unnavigated. Formulary barriers left standing.  A few specific cases come to mind.  A patient was denied access to a potentially life-saving medication with known anaphylaxis risk because a PA was required for an epinephrine pen that was co-prescribed.  A nephrologist stated a patient needed a PA for a common and generic antihypertensive agent.  This has to stop.  Today.

MedAccessCE™ is the curriculum she wished existed — built for the prescribers and nurses who are already doing the work, and need the knowledge to do it better.

Created by Jacqueline S. Marinac, PharmD, CCRC.

One course. Two tracks. One licensing platform.

Clinical capability building built for the access fight

For prescribers

Medication Access in America: Navigating the System — Prescriber Track

A 12-module curriculum covering the full landscape of medication access — from PBM structures and payer dynamics to drug shortages, rare disease funding, and the prescriber as patient advocate.

Enroll on Thinkific
For RNs

Medication Access in America: Navigating the System — RN Track

The same rigorous 12-module curriculum adapted for the nursing role — equipping RNs with the knowledge and tools to advocate for patient access at every point of care.

Enroll on Thinkific
Free Preview Module

See the curriculum firsthand.

The Free Preview includes highlights from Modules 0 and 4 — tracing the drug supply chain from discovery to dispensing, and examining how medication cost shapes adherence and patient outcomes.

Modules 0 & 4
Self-paced preview
No login required
See the Free Preview

Opens on Thinkific — our course platform. Free, no credit card.

Free resources

Three Additional Free Resources to Get You Started

Free White Paper

Evidence-based data on the prior authorization burden — what it costs clinicians, and what to do about it.

Download Free

Health System ROI Calculator

See exactly how much time and revenue your health system recovers annually once your team is trained.

Calculate Your Savings

Health System Readiness Consultation

Connect with us to explore whether MedAccessCE is the right fit for your health system — no obligation, no sales pressure, just a focused conversation about your team's needs.

Take the Readiness Assessment
Before you go

Common Questions

Two licensing paths. One institutional solution.

The Clinical Operations Package puts point-of-care decision tools in every clinician's hands — EHR SmartPhrases, PA scripts, drug shortage protocols, and more. The Certificate Courses build the foundational knowledge behind them. License one or both for your health system.

